Paroxysmal nocturnal hemoglobinuria (PNH) sounds like a spell from a fantasy novel, but it’s actually a rare blood disorder with a very real footprint in everyday life.
The “nocturnal” part is a historical nod to how people often notice dark urine in the morning (because hemoglobin from damaged red blood cells can spill into urine), not a rule that PNH only shows up at night.
PNH is better understood today than everand, importantly, it’s more treatable today than it was a couple decades ago.
This article breaks down what causes PNH, how it affects the body, what the outlook looks like now, and how the condition can ripple into work, school, relationships, and mental bandwidth.
We’ll keep it medically accurate, reader-friendly, and just humorous enough to remind you that your immune system is powerful… and occasionally a bit of an overenthusiastic hall monitor.
What Is PNH, in Plain English?
PNH is an acquired disorder (meaning you don’t inherit it from your parents) that begins in the bone marrowthe body’s blood-cell factory.
A change occurs in a single blood-forming stem cell, and that cell’s “family line” (its clones) starts producing blood cells that are missing key protective surface proteins.
Without those protections, parts of the immune systemespecially the complement systemcan damage red blood cells, and sometimes other blood components.
PNH tends to be discussed as a “triad” of problems:
- Hemolysis (red blood cells breaking down too early)
- Blood clots (thrombosis, which can be serious and unpredictable)
- Bone marrow failure (reduced production of blood cells, sometimes overlapping with aplastic anemia or related disorders)
Not everyone has all three, and symptoms can range from subtle to severe. That variability is one reason PNH can take time to diagnose.
Cause: Why PNH Happens
The “root cause” is a PIGA mutation (but it’s not inherited)
Most PNH starts with a somatic mutation in a gene called PIGA inside a bone marrow stem cell. “Somatic” means it happens after you’re born, in the cells of your bodynot in the egg or spermso it’s not passed down like hair color or dimples.
PIGA is involved in making an anchor (called a GPI anchor) that helps attach certain proteins to the surface of blood cells.
Two of the most important surface “bodyguards” that can be missing are CD55 and CD59. When they’re absent or reduced, blood cellsespecially red blood cellslose protection against the complement system.
Meet complement: your immune system’s security team (with a battering ram)
Complement is a part of the immune system that helps fight infections. Think of it like a neighborhood watch that can call in backup.
In PNH, complement can mistakenly treat your own red blood cells like suspicious strangers and attack them.
The result is red blood cell destruction inside blood vessels (intravascular hemolysis) and, depending on the pathway involved and the therapy used, sometimes destruction that shows up more in the spleen/liver (extravascular hemolysis).
Why blood clots are such a big deal in PNH
PNH is strongly associated with thrombosis (blood clots). These can occur in typical places like leg veins, but PNH is also known for clots in unusual locations (like abdominal veins).
Clot risk is one of the most serious aspects of PNH because clots can lead to organ damage or become life-threatening depending on where they occur.
Researchers have linked clot risk to multiple factors, including complement activation, hemolysis, inflammation, and effects on platelets and blood vessel lining.
The takeaway for readers: in PNH, clot risk isn’t just an “extra complication”it’s central to the condition’s impact and treatment strategy.
How PNH Affects the Body: Symptoms and Complications
Common symptoms (and why they happen)
- Fatigue: Often driven by anemia and chronic inflammation; many patients describe it as “battery stuck at 20%.”
- Shortness of breath, weakness, rapid heartbeat: Classic anemia signals as the body tries to deliver enough oxygen.
- Dark urine (especially in the morning): Can happen when hemoglobin from destroyed red blood cells is filtered into urine.
- Abdominal pain or swallowing difficulties: Sometimes related to smooth muscle effects from free hemoglobin and nitric oxide changes.
- Headaches, chest discomfort: Can appear with anemia, hemolysis, or clot-related issues and always deserve medical attention.
Major complications doctors watch closely
- Thrombosis (blood clots): A feared complication; location and timing can be unpredictable.
- Kidney involvement: Ongoing hemolysis can affect kidney function; some people develop chronic kidney disease over time.
- Bone marrow failure: Low blood counts may overlap with aplastic anemia or related marrow disorders.
- Iron issues: Hemolysis and urine loss can contribute to iron deficiency, while transfusions can sometimes complicate iron balance in other contexts.
Importantly, PNH doesn’t always announce itself with dramatic symptoms. Some people first learn about it after an abnormal lab result, an anemia workup, or evaluation for a clot.
Diagnosis: How Doctors Confirm PNH
Flow cytometry is the gold standard
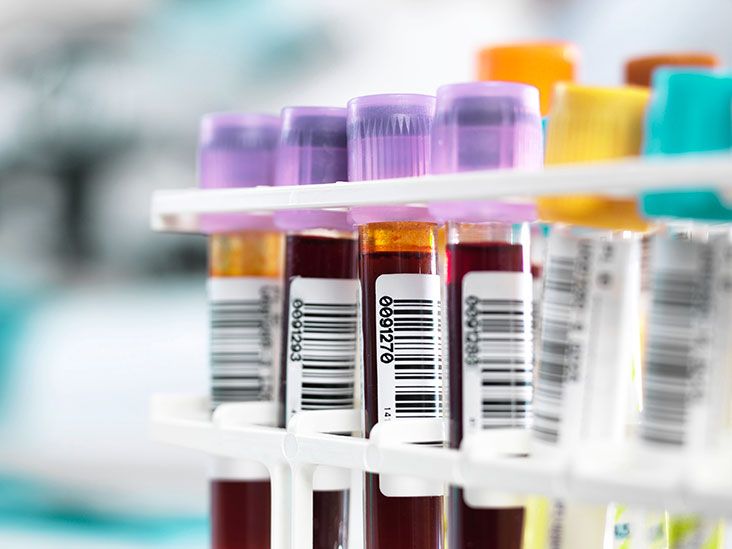
The core diagnostic test for PNH is flow cytometry, which evaluates blood cells for missing or reduced surface proteins linked to the GPI anchor.
In many labs, this includes checking markers like CD55 and CD59 (and sometimes additional assays designed specifically for high sensitivity).
Clinicians often measure the “PNH clone size,” meaning the percentage of blood cells affected. This can help interpret symptoms and guide management, especially when PNH overlaps with bone marrow failure.
Other tests help show the “damage pattern”
Doctors may also order labs to assess hemolysis and anemia (like LDH, bilirubin, haptoglobin, and reticulocyte count), kidney function tests, and iron studies.
If symptoms suggest clot risk, imaging may be used to evaluate for thrombosis.
The specific panel depends on the person’s symptoms, history, and whether PNH is suspected on its own or alongside another marrow disorder.
Treatment: What Can Be Done for PNH Today?
Treatment has changed dramatically over the last two decades. Historically, care leaned heavily on transfusions and managing complications.
Today, therapies that target the complement system can reduce hemolysis and lower clot risk for many patients.
The “best” plan depends on symptom severity, clot history, kidney involvement, marrow function, and individual preferences about dosing schedules and routes.
Complement inhibitors: the main modern strategy
Complement inhibitors are medicines designed to block parts of the complement cascade.
Different drugs block different points in the pathway, which can influence how well they control intravascular vs. extravascular hemolysis, how they’re administered, and how often they’re taken.
-
C5 inhibitors (e.g., eculizumab and ravulizumab) target a later step in the complement cascade and have been foundational therapies for many patients.
Newer options in this category have expanded dosing and administration approaches. - C3 inhibitors (e.g., pegcetacoplan) block a more upstream step and may help in situations where extravascular hemolysis remains an issue.
- Factor B inhibitors (e.g., iptacopan) are also upstream and represent a major shift because they can be taken orally in some cases.
Your hematology team may discuss switching therapies if anemia persists, transfusions continue, “breakthrough” hemolysis occurs, or side effects and lifestyle factors make a change worthwhile.
Vaccinations and infection precautions matter (a lot)
Blocking complement can increase susceptibility to certain infections, especially meningococcal disease.
Vaccination is typically required or strongly recommended before starting certain complement inhibitors, and clinicians often discuss additional risk-reduction steps.
This is a “don’t skip the fine print” areaask your care team what vaccines you need and what symptoms require urgent evaluation.
Supportive care: still important, even with targeted therapy
- Transfusions: Used when anemia is severe or symptomatic.
- Folate supplementation: Sometimes used because ongoing hemolysis can increase folate needs.
- Iron management: Individualizedsome need iron supplementation; others may need careful monitoring depending on transfusion history and labs.
- Anticoagulation: May be considered in certain high-risk scenarios, especially with clot history (decisions are individualized).
- Bone marrow transplant: The only potentially curative option, but generally reserved for select situations due to significant risks.
Outlook: Prognosis and What “Living Longer” Looks Like Now
The outlook for PNH has improved substantially with complement-targeting therapies and better recognition of clot risk.
For many patients, modern treatment can reduce hemolysis, lower transfusion needs, and significantly cut the risk of thrombosis.
But “prognosis” isn’t one-size-fits-all. A few factors that influence outlook include:
- History of thrombosis (clots can shape long-term risk and monitoring)
- Degree of hemolysis and anemia
- Kidney function over time
- Whether bone marrow failure is present (and how severe)
- Response to therapy (including breakthrough hemolysis or persistent symptoms)
The hopeful reality: many people with PNH today can plan careers, families, travel, and long-term goals in ways that would have been much harder before targeted therapies existed.
The practical reality: PNH is still a chronic condition that often requires ongoing monitoring and long-term treatment decisions.
Impact: How PNH Can Affect Daily Life (Beyond the Lab Results)
Energy, productivity, and “invisible” symptoms
Fatigue is one of the most common and frustrating PNH symptoms because it can be persistent, variable, and hard for others to see.
People often describe feeling fine one day and wiped out the next, especially around hemolysis episodes, infections, stress, or changes in sleep.
This unpredictability can affect school performance, work deadlines, parenting, and even social plans that used to be easy.
Scheduling life around treatment
Depending on the therapy, treatment may involve infusions at regular intervals, injections, or oral medication with specific timing.
The schedule can influence travel, work routines, and how comfortable someone feels being away from their medical team.
Even when treatment is working well, the logistics can feel like having a “second calendar” that quietly runs your life.
The mental load of clot vigilance
PNH-associated thrombosis risk can create a background worry: “Is this pain normal, or is it something serious?”
That doesn’t mean people should live in fearbut it does mean education matters.
A good care team equips patients with clear guidance on which symptoms should trigger urgent care, and which can be monitored.
Relationships and communication
Chronic illness changes conversations. You may find yourself explaining lab results to loved ones, negotiating time off with employers, or clarifying why you can’t “just push through” exhaustion.
It helps to have a simple script, like: “My bone marrow makes blood cells that are vulnerable to immune damage, so I have anemia and clot risk. Treatment helps, but I still have flare-ups.”
You don’t owe anyone your entire medical chartjust enough information to get the support you need.
Questions to Ask Your Hematologist
- What is my PNH clone size, and how does it relate to my symptoms?
- Do I have signs of intravascular hemolysis, extravascular hemolysis, or both?
- How are we monitoring clot riskand what symptoms should send me to urgent care?
- Which treatment options fit my medical needs and my lifestyle best (infusion vs. injection vs. oral)?
- Which vaccines do I need before or during complement inhibitor therapy?
- Do I have evidence of bone marrow failure or overlap with aplastic anemia?
Experiences With PNH: What the Journey Can Feel Like (Extended)
The medical definition of PNH fits neatly into textbooks, but the lived experience often looks messiermore like a detective story with plot twists.
Many people describe a “diagnosis odyssey,” where the earliest clues are vague: fatigue that doesn’t match the amount of sleep, shortness of breath going up stairs, headaches that come and go, or lab work that shows anemia without an obvious explanation.
Some notice episodes of dark urine and assume dehydration or something they ate, only to learn later that hemoglobinuria can be part of the picture.
Others don’t suspect anything until a doctor investigates an abnormal LDH or reticulocyte count, ormost dramaticallyuntil a blood clot forces urgent testing.
Once PNH is on the table, flow cytometry can feel like the “final reveal.” People often remember the moment a specialist explains the missing protective proteins on blood cellsbecause it finally turns mystery symptoms into a coherent story.
There can be relief in having a name for what’s happening, mixed with fear because the name is long, rare, and hard to pronounce.
It’s common for patients to say they Googled it, regretted it, then googled it again anyway (because curiosity is undefeated).
The best early support often comes from a hematology team that can translate the science into practical steps: what we’re treating, why we’re treating it, and what “stable” should feel like.
Treatment can change the rhythm of life. Infusion-based therapies may require arranging transportation, time off work, childcare coverage, and a backup plan for days when fatigue hits harder than expected.
People who do well on therapy often describe a slow return of “normal energy,” but not always a full resetmore like upgrading from a dying phone battery to one that reliably lasts the day.
Some notice the biggest improvement in stamina and mental clarity; others celebrate fewer transfusions, fewer hemolysis symptoms, or simply fewer days spent wondering what their body is doing behind their back.
When oral options are part of the plan, the convenience can be real, but so is the responsibility of consistent dosing and follow-up labs.
Another common experience is learning to live with two truths at once: PNH can be serious, and PNH can also be manageable.
People often build a personal “early warning system”not panic, but awareness.
They learn what their anemia feels like, what dehydration does to symptoms, and how infections or stress can amplify fatigue.
For those on complement inhibitors, vaccine appointments and infection education become part of routine health maintenance.
Some patients describe becoming unexpectedly organized: medication reminders, symptom notes, lab portals bookmarked, and a go-to list of questions for appointments.
It’s not that they want to be part-time medical managersit’s that PNH rewards preparation.
Socially and emotionally, PNH can be isolating because most people have never heard of it.
Patients may get tired of explaining why they look “fine” but feel drained, or why they can’t commit to plans weeks in advance.
Over time, many develop a simple communication style: they share the basics, name the biggest risks (like clots), and focus on what helps (like rest, predictable routines, and supportive workplaces).
The people who stick around and learn with them often become a quiet source of stability.
And for many, the biggest win isn’t dramaticit’s getting back to ordinary life: steady workdays, consistent school attendance, travel that doesn’t feel risky, and mornings where the first thought isn’t, “What’s my body going to do today?”
Conclusion
Paroxysmal nocturnal hemoglobinuria is rare, complex, andthanks to modern complement-targeted treatmentsfar more controllable than it once was.
Understanding the cause (an acquired PIGA mutation leading to missing protective surface proteins), the major risks (hemolysis and thrombosis), and the tools available today (flow cytometry for diagnosis and a growing menu of therapies) can help patients and families feel less blindsided.
With good specialty care, many people with PNH can build a long-term plan that prioritizes both safety and quality of lifebecause the goal isn’t just better lab numbers, it’s getting more of your time and energy back.