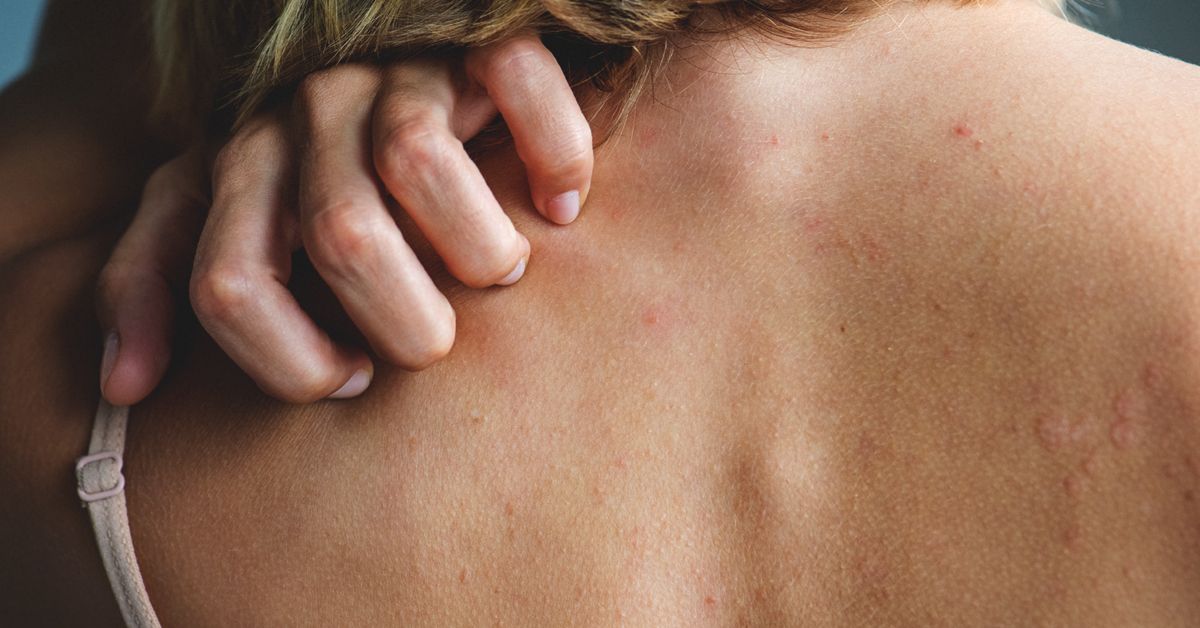
A new medication can be a helpful little overachiever: lower the fever, tame the infection, calm the pain, and send you on your way. But sometimes your skin has other opinions. A drug rash or drug eruption can range from a few itchy pink bumps to a serious, fast-moving reaction that needs emergency care.
The tricky part is that rashes are not great at wearing name tags. A medication rash can resemble eczema, a viral illness, heat rash, acne, hives, or something caused by a new laundry detergent. That is why timing, symptoms, and a complete medication list matter so much. This guide explains common drug rash symptoms, what different eruptions may look like in pictures, possible causes, warning signs, and treatment options.
Important note: A rash after taking a medication should be discussed with a healthcare professional, especially when it is new, widespread, painful, blistering, or accompanied by fever, swelling, or breathing symptoms.
What Is a Drug Rash or Drug Eruption?
A drug rash, also called a drug eruption or medication rash, is a skin reaction linked to a prescription medicine, over-the-counter product, injection, supplement, herbal remedy, or occasionally an illicit substance. Some reactions are caused by an immune-system allergy. Others are nonallergic side effects, sensitivity to sunlight, changes in blood vessels, or direct effects on the skin.
In plain English, the medicine may be doing exactly what it was hired to do for one part of the body while causing a noisy skin protest somewhere else. The reaction may happen within minutes, hours, days, or even weeks after starting a medication. That delay is one reason it can be difficult to identify the culprit.
Drug rashes are not always true drug allergies. A drug allergy involves the immune system reacting to a medication. A nonallergic rash may still be uncomfortable or medically important, but it does not necessarily mean the person is allergic to that drug forever. Correct labeling matters because an inaccurate “allergy” label can limit useful treatment choices later.
Drug Rash Symptoms: What Can It Feel and Look Like?
Symptoms vary widely. Some people notice itching first. Others see a few spots after showering and assume the bathroom lighting has turned against them. A drug eruption can affect a small area or cover much of the body.
Common Medication Rash Symptoms
- Pink, red, purple, gray, or darker patches depending on skin tone
- Small flat spots, slightly raised bumps, or large merged patches
- Itching, burning, stinging, tenderness, or warmth
- Hives or welts that come and go
- Swelling of the lips, eyelids, face, hands, or feet
- Dryness, scaling, or peeling as the rash improves
- Fever, fatigue, swollen lymph nodes, or body aches in more concerning reactions
On lighter skin, inflammation may look pink or red. On medium to deep skin tones, it may appear purple, gray, dark brown, or darker than surrounding skin. The rash may feel warm, itchy, bumpy, or painful even when redness is subtle. This is one reason a person’s symptoms matter just as much as the color visible in a photo.
Drug Rash Pictures: What Different Eruptions Typically Look Like
Pictures of drug rashes can be useful for recognizing patterns, but they cannot confirm a diagnosis. Two rashes can look nearly identical in an image while having very different causes and levels of risk. A clinician considers the rash’s appearance, location, timing, medication history, recent illness, and other symptoms.
Morbilliform or Maculopapular Drug Eruption
This is one of the most common medication rashes. “Morbilliform” means measles-like, though it does not mean you have measles. It often starts as small pink-to-red spots and bumps on the trunk, then spreads symmetrically to the arms, legs, and neck. The spots can merge into larger patches. Itch and a mild fever may occur.
A maculopapular rash often appears about one to two weeks after a first exposure to a medication, although timing varies. If someone takes the same offending medicine again, the reaction may happen sooner. In uncomplicated cases, the mouth, eyes, and genital areas are not involved.
Hives and Angioedema
Hives, also called urticaria, look like raised itchy welts that may change shape or move around over hours. One patch may fade while another pops up somewhere else, behaving like it has a complicated social calendar. Hives can occur alone, but they may also appear with swelling called angioedema.
Angioedema commonly affects the eyelids, lips, tongue, face, hands, or feet. Hives with throat tightness, trouble swallowing, wheezing, faintness, or breathing difficulty can be a sign of anaphylaxis and require emergency care.
Fixed Drug Eruption
A fixed drug eruption usually returns to the same spot each time a person takes the triggering medication. It may look like a round or oval red, dusky purple, or brown patch that can blister or leave lingering dark discoloration. Common locations include the lips, hands, feet, groin, and genital area.
The “fixed” part does not mean the rash has been repaired. It means the reaction has picked a favorite address and tends to revisit it after re-exposure to the medicine.
Photosensitive Drug Rash
Some medications make the skin unusually sensitive to sunlight or ultraviolet light. The rash may look like an exaggerated sunburn, redness, darkening, or an itchy eruption on areas exposed to the sun, such as the face, neck, upper chest, forearms, and backs of the hands.
Photosensitive reactions can occur with certain antibiotics, diuretics, anti-inflammatory medicines, and other drugs. The rash may not appear until sun exposure enters the plot, which makes the cause less obvious.
Pustular Eruption
A pustular drug eruption may cause many small pus-filled bumps, often on red skin. Some cases are mild, while others may be part of a serious reaction called acute generalized exanthematous pustulosis, or AGEP. Fever, widespread redness, and rapid spread should be evaluated urgently.
What Causes Drug Rashes?
Almost any medication can cause a rash, including products that are available without a prescription. Commonly reported triggers include antibiotics, nonsteroidal anti-inflammatory drugs, anti-seizure medicines, allopurinol, blood pressure medicines, chemotherapy drugs, biologic medicines, and some antiviral medications.
That does not mean a medication is “bad” or that everyone who takes it will develop a reaction. Most people tolerate their medicines without trouble. A rash may depend on the specific drug, dose, immune response, genetics, underlying infection, age, other health conditions, or the combination of medicines and supplements being used.
Allergic Versus Nonallergic Medication Reactions
An allergic drug rash occurs when the immune system identifies a medication, or a chemical related to it, as a threat. The reaction may involve hives, itching, swelling, wheezing, or anaphylaxis. In contrast, nonallergic eruptions can happen through other mechanisms. For example, some medications can cause acne-like bumps, bruising, photosensitivity, or skin changes without an immune allergy.
It is also possible for a rash to be unrelated to the medication. Viral infections, fungal infections, autoimmune conditions, contact dermatitis, heat, and other skin disorders can all appear around the same time a person begins treatment. Timing alone is important, but it is not the whole detective story.
When Is a Drug Rash an Emergency?
Most mild rashes are not life-threatening, but severe cutaneous adverse reactions can become dangerous quickly. Seek emergency care or call 911 right away for a rash after a medication that occurs with:
- Trouble breathing, wheezing, throat tightness, or difficulty swallowing
- Swelling of the tongue, lips, mouth, face, or throat
- Fainting, dizziness, confusion, a weak pulse, or signs of shock
- Blisters, peeling skin, or skin that is painful to touch
- Sores in the mouth, eyes, nose, or genital area
- A widespread painful rash with fever, flu-like symptoms, or severe fatigue
- Dark purple spots, rapidly spreading discoloration, or a rash that does not fade when pressed
- Yellowing of the eyes or skin, dark urine, facial swelling, or swollen lymph nodes
Stevens-Johnson Syndrome and Toxic Epidermal Necrolysis
Stevens-Johnson syndrome (SJS) and toxic epidermal necrolysis (TEN) are rare but life-threatening reactions, often linked to medications. They may begin with fever, sore throat, cough, burning eyes, fatigue, or flu-like symptoms. A painful rash can follow, sometimes with blisters, skin detachment, and injury to the mouth, eyes, or genital tissues.
These conditions are medical emergencies. They are not situations for taking a few more photos, opening twelve browser tabs, and hoping the rash becomes less dramatic by breakfast.
DRESS Syndrome
DRESS syndrome stands for drug reaction with eosinophilia and systemic symptoms. It can occur weeks after starting a medication and may involve fever, widespread rash, facial swelling, enlarged lymph nodes, abnormal blood cells, and inflammation of internal organs such as the liver or kidneys.
DRESS requires prompt medical assessment because symptoms can worsen or continue after the suspected medication is stopped. It may involve blood tests, careful monitoring, and specialist treatment.
How Doctors Diagnose a Drug Eruption
There is no single test that instantly identifies every medication rash. Diagnosis usually starts with a detailed timeline. A clinician may ask when each medication began, when doses changed, when the rash appeared, whether you have taken the drug before, and whether you have used over-the-counter products, eye drops, nasal sprays, vitamins, supplements, or herbal remedies.
A medication calendar can be surprisingly useful. Write down every product taken in the prior few weeks, including the start date, dose, last dose, and time symptoms began. Bring photos showing how the rash changed. Photos are particularly helpful if hives come and go before the appointment.
Depending on the symptoms, evaluation may include a skin examination, blood tests, liver or kidney testing, a skin biopsy, allergy assessment, or supervised drug testing in carefully selected cases. Never restart a medication on your own just to see whether the rash returns. Re-challenging a serious reaction can be dangerous.
Drug Rash Treatment Options
Treatment depends on the type and severity of the eruption. The first step is usually to contact the prescriber promptly and determine whether the suspected medication should be stopped, changed, or continued under supervision. Do not abruptly stop a medication that is essential for seizures, heart disease, blood clot prevention, organ transplantation, mental health treatment, or other serious conditions without urgent medical guidance.
Treatment for Mild Drug Rashes
For uncomplicated reactions, a clinician may recommend stopping or replacing the suspected medicine and using symptom relief measures. These may include cool compresses, fragrance-free moisturizers, topical corticosteroid creams, or oral antihistamines for itch when appropriate for the individual.
A mild rash may fade over days after the responsible medicine is discontinued, but the timeline varies. Peeling or temporary color changes can occur as the skin heals. Avoid scratching, harsh exfoliants, fragranced products, and sun exposure that may aggravate irritated skin.
Treatment for Severe Drug Reactions
Serious reactions may require emergency treatment, hospitalization, intravenous fluids, medication to control inflammation, pain management, wound care, eye care, laboratory monitoring, and specialist involvement. Anaphylaxis requires emergency treatment with epinephrine. SJS, TEN, and DRESS require hospital-level care and should never be managed as a routine home rash.
How to Prevent Another Medication Rash
After a confirmed or strongly suspected drug reaction, ask your healthcare professional exactly what should be recorded in your medical record. Note the medication name, the reaction, when it happened, and how severe it was. “Rash” is useful, but “painful blistering rash with mouth sores” gives future clinicians much more meaningful information.
- Tell every healthcare professional and pharmacist about serious drug reactions.
- Keep an updated medication and allergy list on your phone or in your wallet.
- Include prescription drugs, over-the-counter products, vitamins, and herbal supplements.
- Ask whether related medications should also be avoided.
- Do not borrow medicines or take leftover antibiotics from a previous illness.
- Use sun protection when taking medicines known to increase photosensitivity.
Experiences and Practical Lessons From Drug Rash Situations
Many people first notice a medication rash in an ordinary moment: changing clothes, stepping out of the shower, or scratching an itch that suddenly seems determined to win an award for persistence. The common reaction is often confusion. A person may wonder whether the rash came from food, soap, stress, a pet, a new shirt, or the medicine they began several days ago. That uncertainty is normal. Skin reactions are visual, but the cause is not always visible.
One practical lesson is that timing can be more valuable than memory alone. People often remember starting an antibiotic but forget a new pain reliever, sleep aid, supplement, or over-the-counter cold medicine taken around the same time. Keeping a simple list of everything used during the previous month can help a clinician spot patterns. Even products that seem minor, such as medicated eye drops, topical creams, cough syrup, or herbal capsules, deserve a place on the list.
Another common experience is assuming that an itchy rash must be harmless. Itch is common in mild drug eruptions and hives, but intensity does not perfectly predict seriousness. Conversely, a rash that is painful rather than itchy deserves special attention. Painful skin, blisters, fever, facial swelling, mouth sores, eye irritation, or feeling generally ill are not details to shrug off. They are the body’s equivalent of setting off multiple smoke alarms at once.
Photos can help, especially when a rash changes quickly. Taking clear pictures in natural light each day can document whether the eruption is spreading, fading, developing blisters, or changing color. Include a wider photo for location and a closer photo for texture. However, pictures should support medical evaluation, not replace it. A rash can look less alarming on a screen than it feels in real life, particularly on darker skin tones or when the key symptom is pain, warmth, or swelling.
People also learn that “allergy” is a powerful word in a medical record. It can protect someone from a dangerous repeat exposure, but it can also create problems when the history is vague. A childhood note that says “penicillin allergymaybe rash?” may lead to years of avoiding useful antibiotics. Whenever possible, ask for details: What drug caused the reaction? How soon after taking it did symptoms begin? Were there hives, breathing trouble, swelling, blisters, fever, or hospitalization? Was the diagnosis confirmed? Clear information helps clinicians decide whether a medication should be permanently avoided, evaluated by an allergist, or used safely in the future.
The final lesson is simple but important: do not try to tough out a concerning drug rash alone. It is reasonable to seek prompt advice for any new rash after a medication, and it is essential to seek emergency help for severe symptoms. Most medication rashes improve with correct identification and treatment. The goal is not panic; it is smart, timely action before a small skin complaint turns into a much bigger medical problem.
Conclusion
A drug rash can be mild, itchy, and temporary, or it can signal a serious allergic or inflammatory reaction. Look for the pattern: when the medication started, how quickly the rash appeared, where it is spreading, and whether there are warning signs such as fever, swelling, breathing symptoms, painful skin, blisters, or sores in the mouth or eyes.
Do not diagnose a medication rash from pictures alone, and do not restart a suspected medication to “test” the reaction. Contact a healthcare professional promptly, keep a careful medication timeline, and seek emergency care for any signs of anaphylaxis or severe skin involvement.
Note: This article is for general educational purposes and is not a substitute for diagnosis or personalized medical advice. For a suspected severe drug reaction or trouble breathing after a medication, call 911 or seek emergency care immediately.


