Hearing your heartbeat after a tough workout is normal. Hearing it inside only one ear while you are sitting still, answering emails, or trying to fall asleep is a different story. That rhythmic “whoosh-whoosh,” “thump-thump,” or “drum solo nobody asked for” may be pulsatile tinnitus in one ear only, also called unilateral pulsatile tinnitus.
Unlike the more common ringing or buzzing type of tinnitus, pulsatile tinnitus often matches the rhythm of your pulse. Because it can sometimes come from changes in blood flow near the ear, blood vessels in the head or neck, middle ear structures, or pressure around the brain, it deserves a proper medical evaluation. The good news? Many causes are treatable once doctors identify the source. The less fun news? Guessing the cause at home is about as reliable as asking a cat to file your taxes.
This guide explains what one-sided pulsatile tinnitus may mean, possible causes, how doctors diagnose it, treatment options, warning signs, and practical ways to manage the sound while you are waiting for answers.
What Is Pulsatile Tinnitus?
Pulsatile tinnitus is a type of tinnitus where a person hears a rhythmic sound that often keeps time with the heartbeat. People describe it as whooshing, pulsing, beating, rushing, throbbing, fluttering, or a soft washing-machine sound in the ear. It may be constant or come and go. It may be loudest at night, after exercise, when lying on one side, or during moments of stress.
Regular tinnitus usually sounds like ringing, buzzing, hissing, or static and often comes from hearing loss, noise exposure, ear injury, or nerve-related changes. Pulsatile tinnitus is different because it may have a physical sound source, often related to blood flow, pressure, or movement of nearby structures. In some cases, a clinician may even hear the sound with a stethoscope, which is called objective tinnitus. More often, only the person notices it.
Why Would Pulsatile Tinnitus Happen in One Ear Only?
When pulsatile tinnitus affects one ear only, the cause may be located on that side of the head, neck, ear canal, middle ear, inner ear, or nearby blood vessels. A one-sided sound does not automatically mean something dangerous is happening, but it is one of the reasons clinicians take this symptom seriously.
For example, a small change in a vein near the left ear may create a left-sided whooshing sound. A middle ear mass behind the right eardrum may create a right-sided pulse. A narrowed blood vessel, high-riding jugular bulb, sigmoid sinus abnormality, or vascular malformation may also produce a sound that seems to come from only one side.
One-sided pulsatile tinnitus is especially important to evaluate if it is new, persistent, worsening, associated with hearing loss, or accompanied by headache, dizziness, vision changes, weakness, numbness, or trouble speaking.
Common Causes of Pulsatile Tinnitus in One Ear
Pulsatile tinnitus is a symptom, not a diagnosis. The goal is to find out what is making the beat. Causes range from simple and manageable to rare but serious.
1. Blood Flow Changes Near the Ear
Many cases involve turbulent or increased blood flow close to the hearing structures. Blood normally moves silently through arteries and veins. But when flow becomes faster, narrower, irregular, or closer to the ear, the ear may pick it up like a built-in microphone nobody ordered.
Possible blood-flow-related causes include high blood pressure, atherosclerosis, narrowing of arteries, narrowing of veins, vascular loops, and increased blood flow states such as anemia, pregnancy, or overactive thyroid. These conditions can make the pulse more noticeable, especially in quiet rooms.
2. Venous Sinus Stenosis
Venous sinus stenosis means narrowing in one of the large veins that drain blood from the brain. This narrowing can create turbulent flow that produces a pulse-synchronous whooshing sound. Some people notice that gentle pressure on the neck, turning the head, or changing position affects the noise. That does not prove the diagnosis, but it gives doctors a helpful clue.
Venous causes are among the more common explanations for pulsatile tinnitus. Treatment depends on severity and the full clinical picture. Some cases are observed, while others may require medication, management of intracranial pressure, or procedures such as venous sinus stenting in carefully selected patients.
3. Idiopathic Intracranial Hypertension
Idiopathic intracranial hypertension, often shortened to IIH, happens when pressure around the brain is elevated without a clear tumor or mass causing it. Pulsatile tinnitus can be one symptom. Other possible signs include headaches, blurry vision, brief vision blackouts, double vision, or swelling of the optic nerve seen during an eye exam.
IIH needs medical attention because vision can be affected. Treatment may include weight management when appropriate, medications that reduce cerebrospinal fluid production, treatment of associated venous narrowing, and close follow-up with neurology and ophthalmology.
4. Dural Arteriovenous Fistula
A dural arteriovenous fistula is an abnormal connection between arteries and veins in the tough outer covering of the brain. It is rare, but it is one of the reasons doctors do not shrug off new pulsatile tinnitus. Some fistulas can increase the risk of bleeding or stroke-like complications, depending on their drainage pattern.
Symptoms may include one-sided pulsatile tinnitus, headache, neurologic symptoms, eye redness or swelling, or a sound that a clinician can hear over the skull. Diagnosis often requires specialized imaging. Treatment may involve endovascular embolization, surgery, radiation, or observation, depending on the specific type.
5. Carotid Artery Disease or Dissection
The carotid arteries carry blood through the neck to the brain. Narrowing, plaque buildup, aneurysm, or a tear in the artery wall called dissection can sometimes cause pulsatile tinnitus. A carotid dissection may occur after trauma, sudden neck movement, or sometimes without a clear trigger.
Warning signs may include sudden neck pain, headache, drooping eyelid, unequal pupils, weakness, numbness, vision problems, or trouble speaking. These symptoms need urgent medical care.
6. Glomus Tumors and Other Head or Neck Tumors
Glomus tumors, also called paragangliomas, are usually noncancerous but can be locally invasive and highly vascular. When they occur near the middle ear or jugular bulb, they may create pulsatile tinnitus in one ear. A doctor may see a reddish or bluish mass behind the eardrum during an exam.
Treatment may include monitoring, surgery, radiation therapy, or specialized procedures to reduce blood flow to the tumor before surgery. The plan depends on size, location, growth, symptoms, and the patient’s overall health.
7. Middle Ear or Inner Ear Conditions
Some ear-related problems can make internal body sounds louder. Earwax blockage, fluid behind the eardrum, middle ear infection, Eustachian tube dysfunction, otosclerosis, and superior canal dehiscence may contribute to unusual ear sounds. These causes may also come with ear fullness, muffled hearing, dizziness, sound sensitivity, or hearing your own voice unusually loudly.
Superior canal dehiscence is a rare condition involving a small opening in the bone over part of the inner ear balance canal. It can cause hearing and balance symptoms, including sensitivity to internal sounds. Treatment may be conservative or surgical if symptoms are severe.
8. High Blood Pressure, Anemia, or Thyroid Disease
Not every cause is exotic. Sometimes the body’s “plumbing pressure” is simply too high or the blood is moving faster than usual. High blood pressure can make vascular sounds more noticeable. Anemia can increase cardiac output because the body is working harder to deliver oxygen. Hyperthyroidism can speed up metabolism and circulation.
These conditions are usually checked with blood pressure measurement and basic lab tests when symptoms and history point in that direction. Treating the underlying condition may reduce or stop the sound.
When Should You See a Doctor?
You should schedule a medical evaluation if you have pulsatile tinnitus in one ear that is new, persistent, worsening, or interfering with sleep and concentration. Start with a primary care clinician, ear, nose, and throat specialist, or audiologist depending on access and symptoms.
Seek urgent care immediately if pulsatile tinnitus comes with sudden hearing loss, severe headache, weakness, numbness, facial drooping, vision loss, double vision, trouble speaking, chest pain, shortness of breath, fainting, or sudden severe neck pain. Those symptoms are not “wait and see” material.
How Doctors Diagnose One-Sided Pulsatile Tinnitus
Diagnosis usually begins with a detailed history. The clinician may ask when the sound started, whether it matches your pulse, whether it is in one ear or both, what makes it better or worse, whether neck pressure changes it, and whether you have headache, dizziness, hearing loss, vision changes, or neurologic symptoms.
The physical exam may include checking blood pressure, looking inside the ear, listening over the neck and skull with a stethoscope, and examining the head, neck, jaw, and neurologic system. An audiogram may test hearing, and tympanometry may check middle ear function.
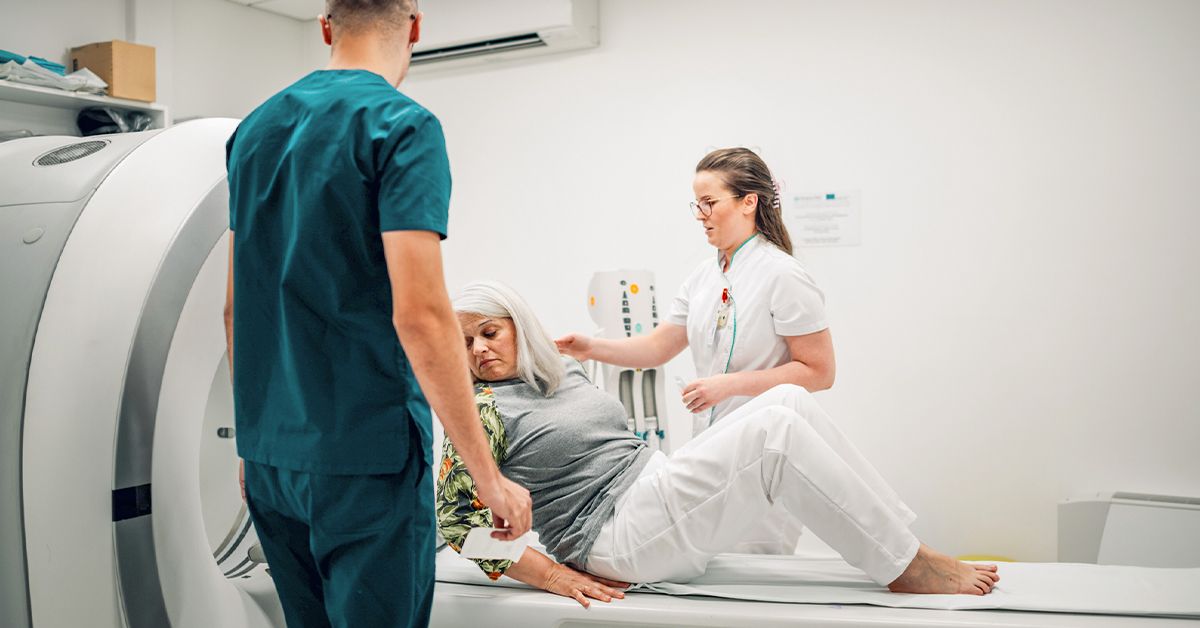
Imaging is often important for unilateral or pulsatile tinnitus. Depending on the suspected cause, doctors may order CT angiography, CT venography, MRI, MR angiography, MR venography, CT of the temporal bone, carotid ultrasound, or digital subtraction angiography. These tests can look at blood vessels, skull base structures, the middle and inner ear, and possible masses.
Treatment Options for Pulsatile Tinnitus in One Ear
Treatment depends entirely on the cause. There is no single magic pill for pulsatile tinnitus, which is unfortunate because “one magic pill” would be excellent branding.
Treating Blood Pressure and Circulation Problems
If high blood pressure, anemia, thyroid disease, or another systemic condition is contributing, treatment focuses on that condition. This may include blood pressure medication, iron therapy when appropriate, thyroid treatment, lifestyle changes, or management of cardiovascular risk factors.
Treating Ear and Middle Ear Problems
If the cause is earwax, fluid, infection, or Eustachian tube dysfunction, treatment may include safe earwax removal, medication, observation, or treatment of allergies or infection. Never dig aggressively in the ear canal with cotton swabs or ear candles. The ear canal is not a tunnel for DIY archaeology.
Procedures for Vascular Causes
Some vascular causes may be treated with endovascular procedures performed through blood vessels. Examples include embolization for certain fistulas or malformations, stenting for selected venous sinus stenosis, or treatment of aneurysms or significant artery disease. These decisions require specialist evaluation and careful imaging review.
Surgery or Radiation for Tumors
If a glomus tumor or other mass is found, treatment may involve monitoring, surgery, radiation therapy, or a combination. The best option depends on the tumor’s size, growth rate, location, symptoms, and risk to nearby nerves and blood vessels.
Sound Therapy and Coping Strategies
When the cause is not found or cannot be fully corrected, symptom management matters. Background sound, white noise, fans, sound machines, hearing aids, tinnitus counseling, cognitive behavioral therapy, relaxation techniques, and sleep strategies may help reduce the impact. These approaches do not “erase” the sound, but they can lower the brain’s alarm response to it.
Can Pulsatile Tinnitus Go Away?
Yes, pulsatile tinnitus can go away when the underlying cause is temporary or treatable. For example, tinnitus related to middle ear fluid, anemia, or blood pressure changes may improve after treatment. Vascular causes may improve after targeted procedures. In other cases, the sound may persist but become less intrusive with management and time.
The key is not to assume. Because one-sided pulsatile tinnitus may point to a treatable condition, evaluation is better than trying to out-stubborn the noise.
Practical Tips While Waiting for an Appointment
Keep a symptom diary. Note when the sound appears, which ear is affected, whether it matches your pulse, what position makes it louder, and whether exercise, caffeine, alcohol, stress, or sleep changes affect it. Record your blood pressure if you have a home monitor.
Use gentle background sound at night, such as a fan, soft music, rain sounds, or a white noise machine. Avoid total silence if silence makes the beat feel louder. Protect your hearing from loud noise, but do not overuse earplugs in quiet places because that may make internal sounds more noticeable.
Limit panic-searching online at 2 a.m. The internet is very good at turning a mild symptom into a blockbuster disaster movie. Use reputable medical sources and let proper testing guide the next steps.
Experience-Based Notes: What One-Sided Pulsatile Tinnitus Can Feel Like
People who experience pulsatile tinnitus in one ear often describe it as strangely specific. It is not just “my ears are ringing.” It may feel like a tiny heartbeat has moved into the left ear and signed a long-term lease. Some notice it first at night when the room is quiet. Others hear it while lying on one side, bending over, climbing stairs, or recovering after exercise. The sound may be soft enough to ignore during the day but loud enough at bedtime to become the main character.
A common experience is uncertainty. Because the sound often matches the pulse, many people check their wrist or neck and realize the ear noise is synchronized with the heartbeat. That discovery can be reassuring because it explains the rhythm, but it can also be alarming. The mind naturally asks, “Why am I hearing blood flow in only one ear?” That question is exactly why medical evaluation is useful.
Another common experience is frustration during the diagnostic process. A person may have a normal ear exam, normal hearing test, or symptoms that come and go. That does not mean the sound is imaginary. Pulsatile tinnitus can be real even when the first exam looks normal. Some causes are located deeper in blood vessels, venous sinuses, or skull base structures, which is why imaging may be needed.
Sleep can become the hardest part. In a quiet bedroom, the brain has fewer external sounds to focus on, so the pulsing can feel louder. Many people find that low-level background sound helps. A fan, sound machine, soft podcast, or rainfall track may give the brain something neutral to process. The goal is not to drown out the sound with loud noise. The goal is to soften the contrast between silence and the pulse.
Stress often makes the experience worse, even when stress is not the root cause. When the nervous system is on high alert, the brain monitors the body more closely. A small whoosh can become impossible to ignore. Relaxation exercises, slow breathing, stretching the neck and jaw, and consistent sleep routines may reduce the distress around the sound. They are not a substitute for diagnosis, but they can make daily life more manageable.
Work and concentration can also be affected. Some people feel distracted during quiet tasks like reading, writing, studying, or computer work. Light background music or ambient sound may help. Others prefer scheduled breaks, hydration, and posture adjustments, especially if neck tension seems to increase awareness of the sound.
The most helpful mindset is balanced: take the symptom seriously without assuming the worst. One-sided pulsatile tinnitus can come from treatable, non-dangerous causes, but it can also signal conditions that deserve prompt attention. Getting evaluated is not overreacting. It is simply the smart move when your ear starts acting like a tiny cardiology department.
Conclusion
Pulsatile tinnitus in one ear only is a rhythmic sound that often matches the heartbeat and seems to come from one side. It may be caused by blood flow changes, venous narrowing, high blood pressure, anemia, thyroid disease, middle ear problems, inner ear conditions, tumors, or rare vascular abnormalities such as dural arteriovenous fistulas. Because some causes are treatable and a few can be serious, persistent one-sided pulsatile tinnitus should be evaluated by a healthcare professional.
Diagnosis may involve an ear exam, hearing test, blood pressure check, lab work, and imaging such as CT, MRI, CTA, MRA, CTV, or MRV. Treatment depends on the cause and may include medication, ear treatment, vascular procedures, surgery, radiation, or tinnitus coping strategies. While waiting for care, symptom tracking and gentle background sound can help reduce stress and improve sleep.
Note: This article is for educational purposes only and does not replace medical advice, diagnosis, or treatment. Anyone with new, one-sided, worsening, or pulse-synchronous tinnitus should consult a qualified healthcare professional.