Note: This article is for educational purposes only and does not replace medical advice. If you have chest pain, fainting, severe shortness of breath, or a very fast heartbeat that does not settle within a few minutes, seek urgent medical care.
What Is Ectopic Atrial Tachycardia?
Ectopic atrial tachycardia, often shortened to EAT, is a type of abnormal heart rhythm that starts in the atria, the two upper chambers of the heart. In a normal heartbeat, the electrical signal begins in the sinus node, the heart’s built-in pacemaker. In EAT, another spot in the atria decides it would like to run the show. Unfortunately, it has the timing skills of a toddler with a drum set.
The word ectopic means “out of place.” In this condition, the extra electrical signal begins outside the sinus node. The word tachycardia means a fast heart rhythm, usually more than 100 beats per minute at rest. In many cases of atrial tachycardia, the heart may beat much faster, sometimes in the range of 150 to 200 beats per minute during an episode.
Ectopic atrial tachycardia is part of a larger group of rhythm disorders called supraventricular tachycardias, or SVTs. “Supraventricular” simply means the rhythm begins above the ventricles, the lower pumping chambers of the heart. While that sounds like a complicated cardiology spelling bee word, the main idea is simple: the heart’s upper chambers are firing too quickly because of an abnormal electrical focus.
How the Heart’s Electrical System Normally Works
Your heart is not just a muscle; it is also an electrical masterpiece. A normal heartbeat starts in the sinus node, located in the right atrium. The signal spreads through the atria, pauses briefly at the atrioventricular node, and then travels into the ventricles. This carefully timed sequence lets the chambers fill and pump efficiently.
With ectopic atrial tachycardia, a different group of cells in the atria begins sending signals faster than the sinus node. This can create a rhythm that is too fast, too persistent, or oddly timed. The ventricles may still follow many of those signals, which is why the pulse can feel like it suddenly switched from “calm stroll” to “sprinting for the bus.”
Focal vs. Multifocal Atrial Tachycardia
Many people use the term ectopic atrial tachycardia to describe focal atrial tachycardia, where the abnormal rhythm comes from one specific spot in the atria. There is also multifocal atrial tachycardia, where several atrial spots are firing abnormal signals. Multifocal atrial tachycardia is often associated with lung disease and is treated differently because the problem is not coming from one neat little troublemaker.
Common Symptoms of Ectopic Atrial Tachycardia
Some people with EAT barely notice it. Others feel every beat like their heart is trying to tap out a dramatic movie soundtrack. Symptoms vary depending on the heart rate, how long the rhythm lasts, whether the person has other heart disease, and how well the body tolerates the fast rhythm.
Symptoms in Adults
Common symptoms of ectopic atrial tachycardia may include:
- Heart palpitations or a racing heartbeat
- Fluttering, pounding, or “skipping” sensations in the chest
- Dizziness or lightheadedness
- Shortness of breath
- Chest discomfort or pressure
- Fatigue, especially during activity
- Feeling anxious because the heartbeat feels unusual
- Fainting or near-fainting in more serious cases
Symptoms may come and go, or the rhythm may be more persistent. Some episodes begin suddenly, while others build gradually. That gradual “warm-up” pattern can help doctors distinguish atrial tachycardia from some other SVTs that start and stop like someone flipped a light switch.
Symptoms in Babies and Children
Children cannot always explain palpitations, and babies definitely cannot say, “Excuse me, my atrial rhythm appears ectopic today.” Instead, caregivers may notice subtle signs such as poor feeding, sweating with feeds, rapid breathing, unusual tiredness, vomiting, irritability, or poor weight gain. In some children, the rhythm is discovered during a routine exam when a clinician hears or measures a very fast heart rate.
Persistent EAT in children deserves careful attention because a fast rhythm that continues for a long time can weaken the heart muscle, a condition sometimes called tachycardia-induced cardiomyopathy. The good news is that when the rhythm is controlled, heart function can often improve.
What Causes Ectopic Atrial Tachycardia?
Ectopic atrial tachycardia happens when atrial cells outside the sinus node become electrically overactive. The exact reason can differ from person to person. Sometimes there is a clear trigger. Other times, the heart simply has a small electrical focus that behaves like it drank three espressos and joined a marching band.
Possible Causes and Risk Factors
Potential causes and contributing factors include:
- Heart surgery: Some atrial tachycardias occur after surgery because scar tissue can affect electrical pathways.
- Congenital heart disease: People born with structural heart differences may have a higher risk of rhythm problems.
- Heart muscle disease: Cardiomyopathy or inflammation can irritate the heart’s electrical system.
- High blood pressure or coronary artery disease: These conditions can change the structure and function of the heart over time.
- Infections or acute illness: Fever, inflammation, dehydration, or stress on the body may trigger fast rhythms.
- Pregnancy: Hormonal shifts, increased blood volume, and cardiovascular strain may make some arrhythmias more noticeable.
- Stimulants: Excess caffeine, nicotine, certain decongestants, energy drinks, or stimulant medications may worsen palpitations in sensitive people.
- Thyroid disease: An overactive thyroid can increase heart rate and trigger arrhythmias.
- Electrolyte imbalance: Low potassium, magnesium problems, or dehydration can make the heart more irritable.
In some cases, EAT is called automatic atrial tachycardia because the abnormal focus fires on its own. In other cases, the rhythm may involve triggered electrical activity or a tiny reentry circuit. Doctors do not always need to identify the exact microscopic mechanism before treating the condition, but understanding the rhythm pattern helps guide care.
How Ectopic Atrial Tachycardia Is Diagnosed
Diagnosis begins with a medical history, a symptom review, a physical exam, and documentation of the rhythm. The key phrase is “documentation.” A person can describe palpitations beautifully, but doctors need to catch the rhythm on a monitor to know exactly what is happening. The heart is sneaky like that.
Electrocardiogram
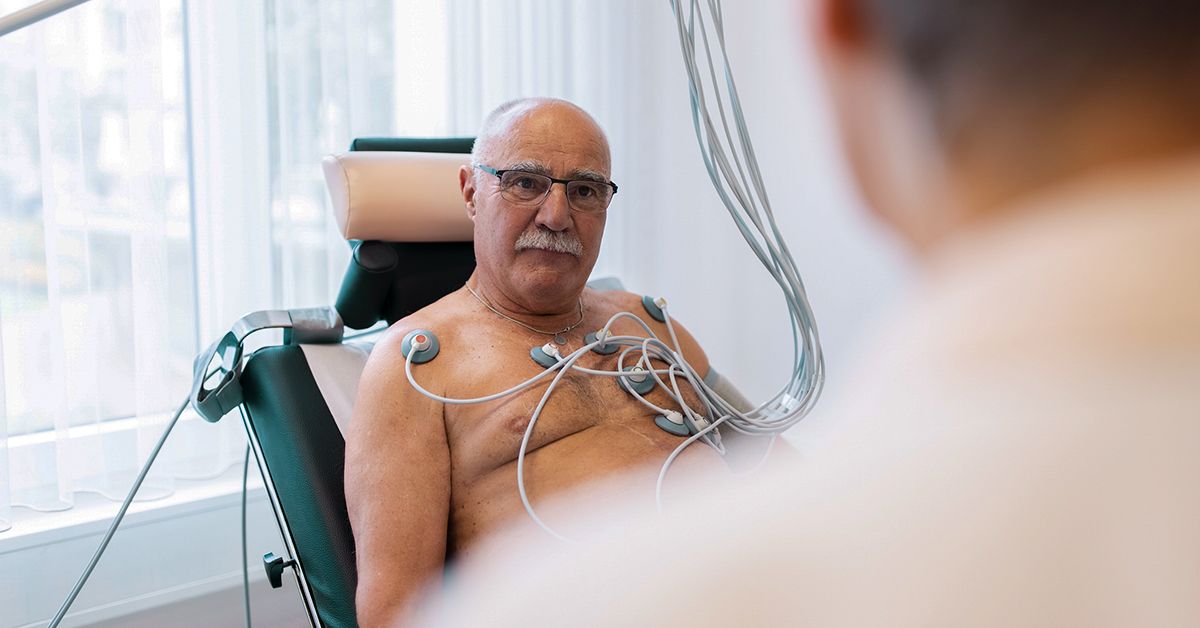
An electrocardiogram, or ECG/EKG, records the heart’s electrical activity. In focal atrial tachycardia, the ECG may show abnormal P waves, which represent atrial activation. The P waves may look different from normal sinus rhythm because the signal is starting from a different atrial location.
Holter or Event Monitor
If the rhythm comes and goes, a short office ECG may miss it. A Holter monitor records heart rhythm continuously, often for 24 to 48 hours. An event monitor or patch monitor may be worn longer, sometimes for one to two weeks or more. These devices help match symptoms with rhythm changes.
Echocardiogram
An echocardiogram uses ultrasound to look at the heart’s structure and pumping function. This test helps doctors check for congenital heart disease, valve issues, chamber enlargement, or reduced heart function caused by persistent tachycardia.
Blood Tests
Blood tests may check thyroid function, electrolytes, infection markers, anemia, or medication levels. These tests do not diagnose EAT directly, but they can reveal triggers that make the rhythm worse.
Electrophysiology Study
An electrophysiology study, often called an EP study, maps the electrical signals inside the heart. Thin catheters are inserted through blood vessels and guided to the heart. This test may be used when symptoms are significant, medication is not working, or catheter ablation is being considered.
Treatment Options for Ectopic Atrial Tachycardia
Treatment depends on symptoms, heart rate, episode frequency, age, overall health, heart structure, and whether the rhythm is brief or persistent. Not every person needs aggressive treatment. Some need observation and trigger management. Others need medication or a procedure to restore rhythm control.
1. Observation and Monitoring
If episodes are rare, mild, and not associated with heart dysfunction, a clinician may recommend monitoring. This does not mean ignoring the condition. It means watching carefully, documenting episodes, and checking whether the rhythm changes over time.
2. Treating Triggers
Sometimes the best treatment is correcting the thing that irritated the heart in the first place. This may include treating fever, dehydration, infection, thyroid disease, anemia, or electrolyte imbalance. Reducing stimulant intake may also help some patients. The heart appreciates fewer surprise energy-drink concerts.
3. Medications
Medications may be used to slow the heart rate, reduce symptoms, or prevent episodes. Common options may include:
- Beta-blockers: These reduce the effect of adrenaline-like signals on the heart and may slow the rate.
- Calcium channel blockers: Certain types, such as diltiazem or verapamil, may help control heart rate in selected patients.
- Antiarrhythmic drugs: These medications act more directly on the heart’s electrical system and require careful medical supervision.
The right medication depends on the person. What works well for one patient may not be safe or effective for another, especially in children, pregnant patients, or people with structural heart disease. This is why rhythm specialists, called electrophysiologists, are often involved.
4. Acute Treatment During a Fast Episode
If a fast rhythm causes severe symptoms, low blood pressure, chest pain, or fainting, urgent treatment may be needed. In some SVTs, vagal maneuvers or medications can help slow or stop the rhythm. However, focal atrial tachycardia does not always respond the same way as other SVTs because it may not depend on the AV node to continue. In unstable situations, electrical cardioversion may be considered by medical professionals.
5. Catheter Ablation
Catheter ablation is a procedure that targets the abnormal electrical focus. During the procedure, an electrophysiologist maps the rhythm and then uses energy, often radiofrequency heat or sometimes freezing, to disable the tiny area causing the problem.
Ablation may be recommended when EAT is recurrent, symptomatic, difficult to control with medication, or causing tachycardia-induced cardiomyopathy. For many people, ablation offers the possibility of long-term rhythm control without daily medication. It is not the right choice for every patient, but when the abnormal focus can be safely mapped, it can be a powerful option.
6. Treatment in Children
Pediatric EAT is managed carefully because children’s hearts, sizes, and medication responses differ from adults. Some children respond well to medication. Others, especially older or larger children with persistent rhythm problems, may be considered for EP study and catheter ablation. The decision balances symptom severity, heart function, medication side effects, and procedural risks.
When Is Ectopic Atrial Tachycardia Serious?
EAT is often manageable, and many cases are not immediately dangerous. However, it should not be brushed off like a spam email from your own heartbeat. Persistent fast rhythm can strain the heart. Over time, some patients may develop reduced pumping function, especially if the tachycardia is continuous or nearly continuous.
Seek urgent medical help if a fast heartbeat is accompanied by chest pain, fainting, severe shortness of breath, confusion, blue lips, severe weakness, or symptoms that last longer than a few minutes and feel intense. Children and infants should be evaluated promptly if they have rapid breathing, poor feeding, unusual sleepiness, sweating with feeds, or a very fast heart rate.
Living With Ectopic Atrial Tachycardia
Living with EAT often means learning your patterns. Some people notice episodes after poor sleep, dehydration, stress, alcohol, caffeine, or illness. Others cannot identify a trigger, which is annoying but common. Keeping a symptom diary can help. Write down the time, activity, heart rate if available, symptoms, food or drink intake, medications, and how long the episode lasted.
Practical Daily Tips
- Stay hydrated, especially during hot weather or exercise.
- Ask your clinician whether caffeine, energy drinks, or decongestants may affect your rhythm.
- Sleep consistently, because tired bodies can be dramatic bodies.
- Manage stress with realistic tools such as breathing exercises, walking, journaling, or counseling.
- Take prescribed medications exactly as directed.
- Do not stop heart rhythm medication suddenly unless your clinician tells you to.
- Bring monitor results, ECGs, and medication lists to cardiology visits.
Smartwatches and phone-based heart devices can be useful for noticing patterns, but they are not a replacement for medical-grade rhythm diagnosis. A watch may tell you your heart rate is high, but an ECG tells the clinician what rhythm is causing it.
Experiences Related to Ectopic Atrial Tachycardia
People who experience ectopic atrial tachycardia often describe the first episode as confusing. One moment they are sitting at a desk, walking through a grocery store, or trying to fall asleep, and the next moment their heart feels like it has discovered a hidden turbo button. The sensation can be frightening, especially when it appears without warning. Even when EAT is not dangerous in that specific moment, the feeling of a racing heart can make anyone wonder whether something serious is happening.
A common experience is the “Is this anxiety or my heart?” puzzle. Palpitations can trigger anxiety, and anxiety can make palpitations feel stronger. That does not mean symptoms are imaginary. It means the heart and brain are excellent at forming a noisy group chat. Patients often feel relieved when a monitor finally captures the rhythm because it gives a name to the experience. Having a diagnosis can turn a mysterious body alarm into a manageable medical condition.
Another frequent experience is frustration with intermittent symptoms. A person may feel dramatic palpitations at home, then arrive at the clinic with a perfectly normal ECG. This is not unusual. Many arrhythmias are episodic. Longer monitoring can help catch the rhythm. Patients often learn to write down details, use approved heart-rate tracking tools, and report patterns clearly. The more specific the information, the easier it is for clinicians to connect the dots.
Some patients describe lifestyle adjustments as trial and error. One person may notice episodes after too much coffee; another can drink coffee without trouble but gets symptoms after poor sleep or dehydration. Some discover that cold medicines containing stimulants make palpitations worse. Others find no obvious trigger at all. The goal is not to live like a fragile porcelain teacup. The goal is to understand what your heart tolerates and what makes it complain loudly.
Medication experiences also vary. Beta-blockers may reduce racing episodes for one patient but cause fatigue for another. Calcium channel blockers may work well for selected adults but may not be appropriate for everyone. Antiarrhythmic medications can be effective, yet they require careful follow-up because they influence the heart’s electrical behavior. Patients should feel comfortable asking why a medication was chosen, what side effects to watch for, and when to call the office.
For people who undergo catheter ablation, the experience often begins with nervousness about the procedure. That is completely understandable. The idea of catheters mapping the heart sounds like science fiction with hospital socks. Many patients, however, appreciate that ablation targets the source of the rhythm rather than simply covering up symptoms. Recovery experiences differ, but patients are usually given clear instructions about activity limits, incision care, and follow-up monitoring.
Parents of children with EAT often describe a different kind of stress. Babies and young children cannot explain palpitations, so parents may watch for feeding problems, fast breathing, sweating, or unusual tiredness. Pediatric cardiology follow-up can feel overwhelming at first, but it also gives families a plan. For many parents, understanding the rhythm, knowing warning signs, and having a treatment pathway makes the condition feel less frightening.
The biggest emotional lesson many patients report is that a rhythm diagnosis changes how they listen to their body. They learn which symptoms are urgent, which are manageable, and which deserve a non-emergency message to the cardiology team. Ectopic atrial tachycardia can be unsettling, but with proper diagnosis, monitoring, and treatment, many people return to normal routines with more confidence and fewer surprise drum solos from the atria.
Conclusion
Ectopic atrial tachycardia is a fast heart rhythm that begins outside the heart’s normal pacemaker in the atria. It may cause palpitations, dizziness, shortness of breath, fatigue, chest discomfort, or fainting, though some people have few symptoms. Causes can include abnormal electrical automaticity, heart surgery, congenital heart disease, thyroid problems, electrolyte imbalance, infection, pregnancy, stimulants, or underlying heart conditions.
The most important step is getting the rhythm documented with an ECG or heart monitor. From there, treatment may involve observation, trigger management, medication, or catheter ablation. Persistent EAT deserves attention because long-running tachycardia can weaken the heart muscle. The encouraging news is that ectopic atrial tachycardia is often treatable, and many people do well with a personalized plan from a cardiologist or electrophysiologist.